Opening: a night shift, a stubborn scope, and a clear question
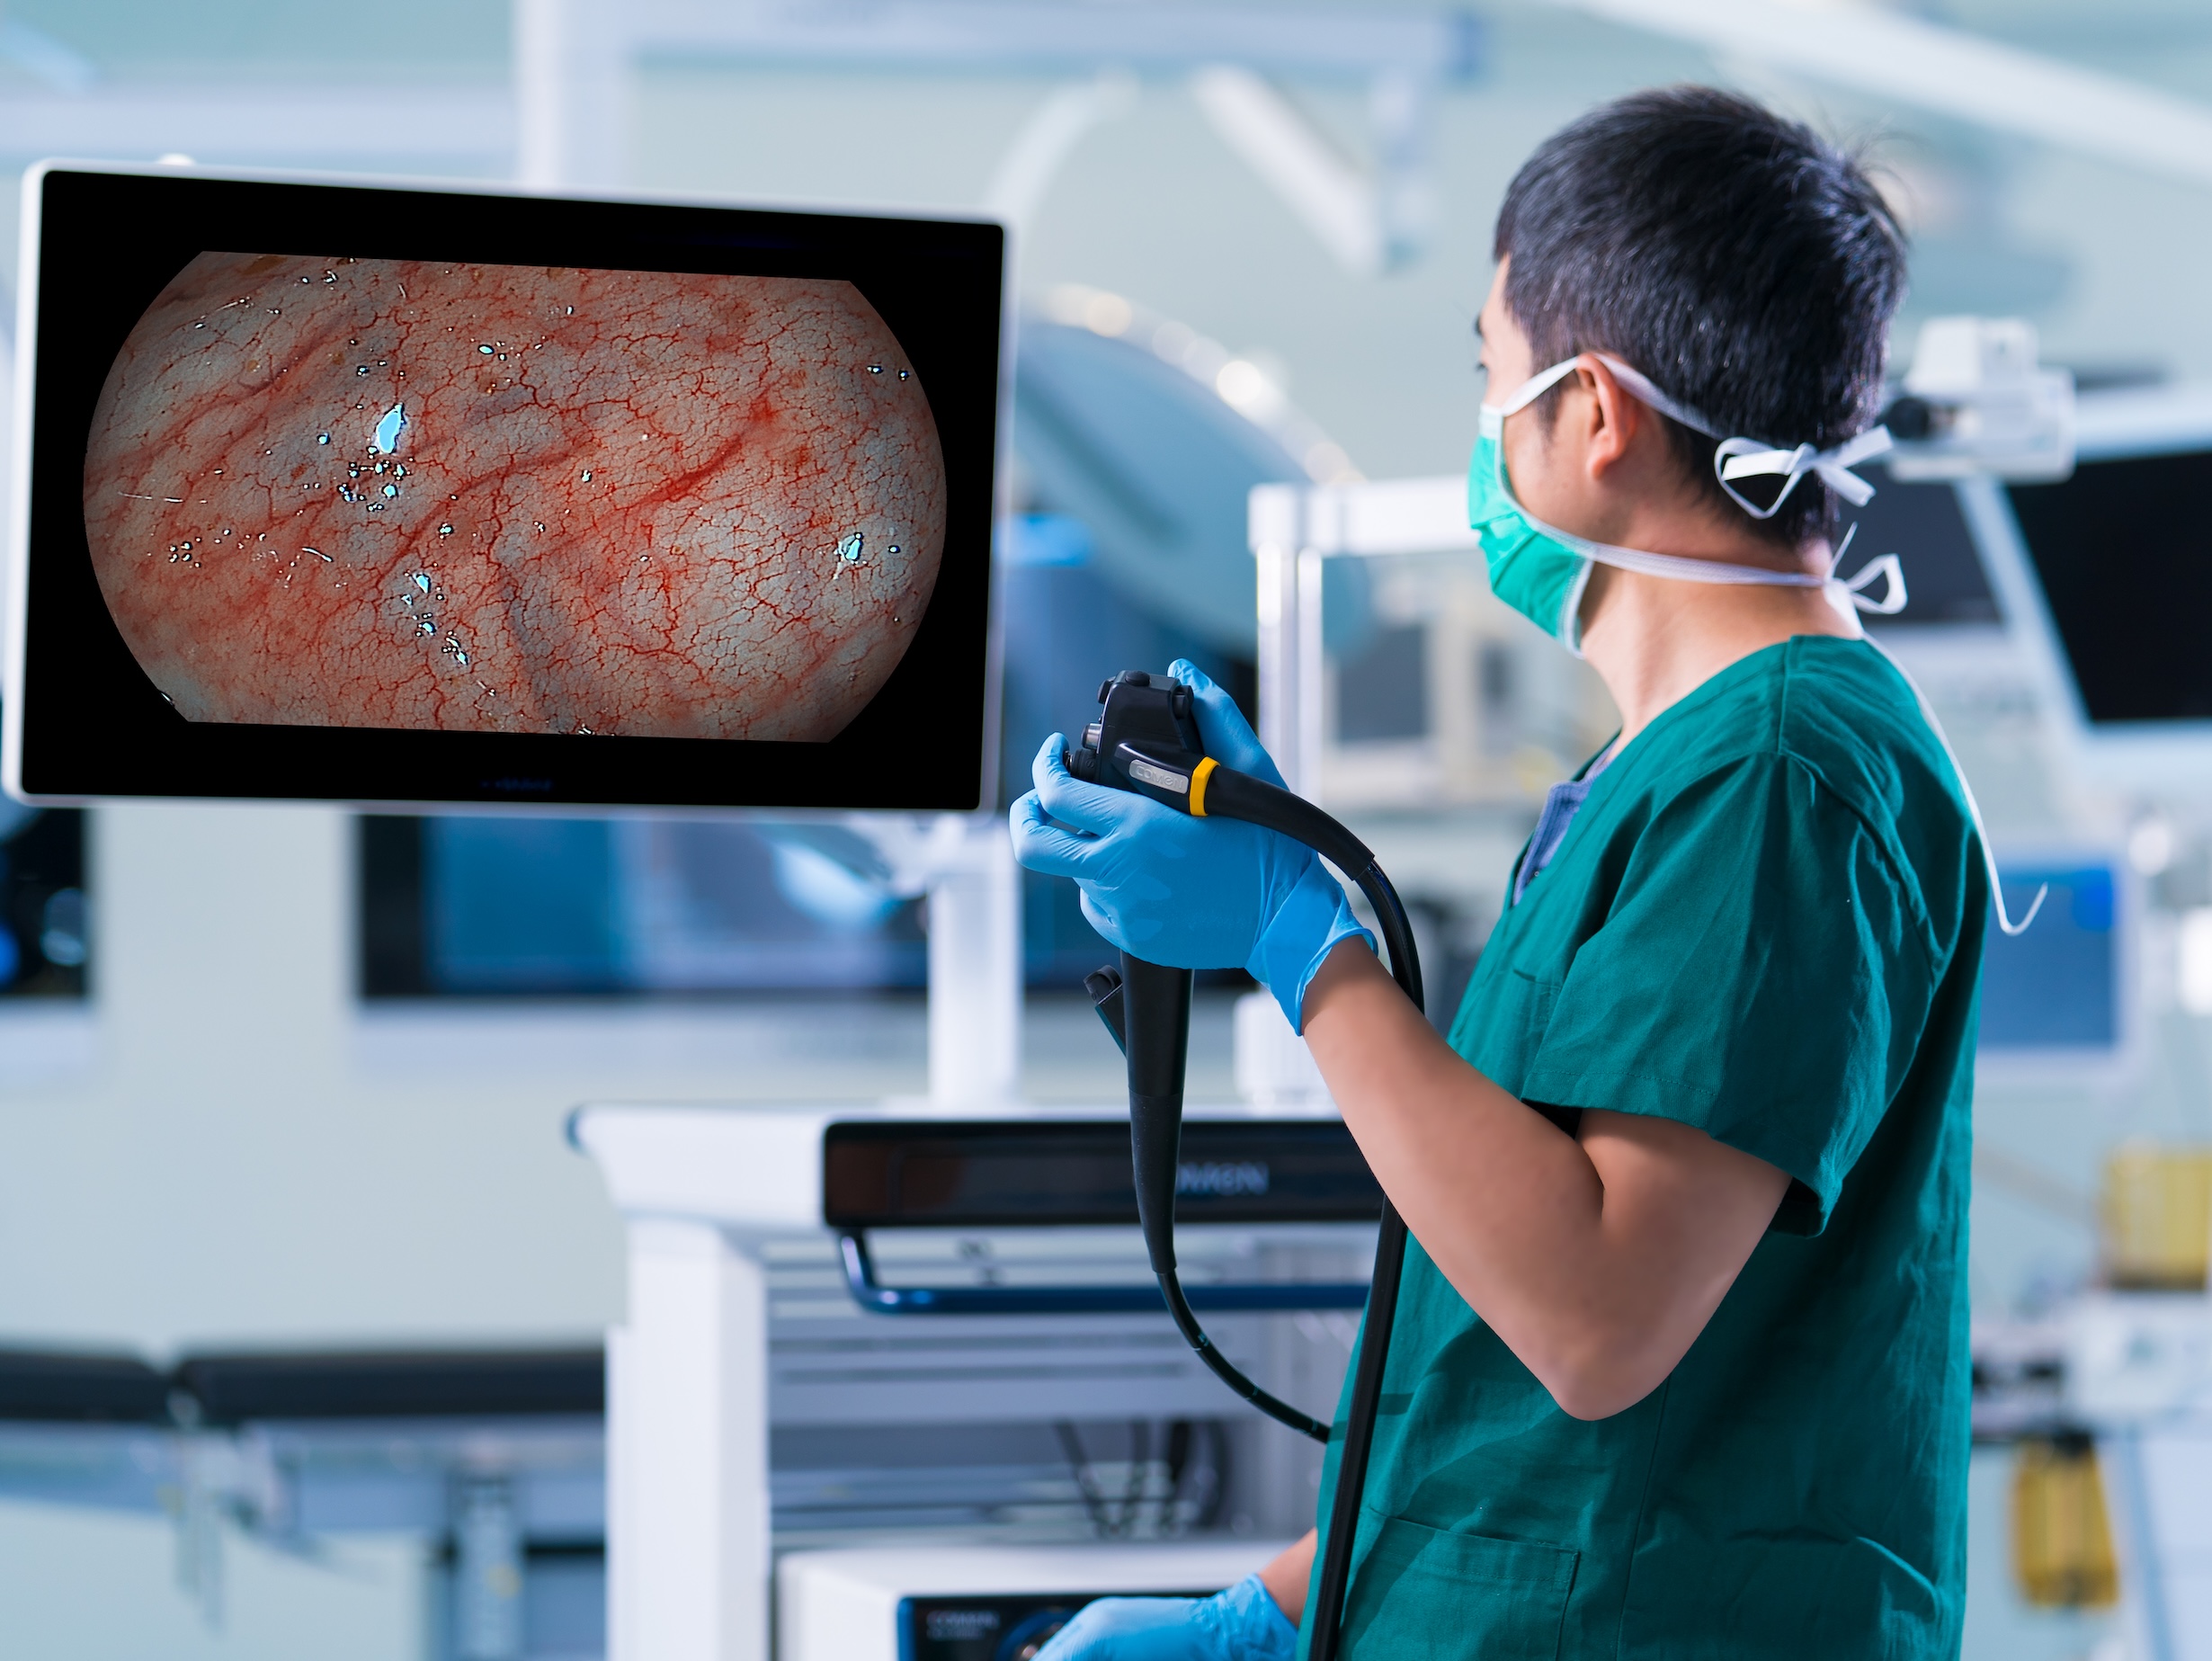
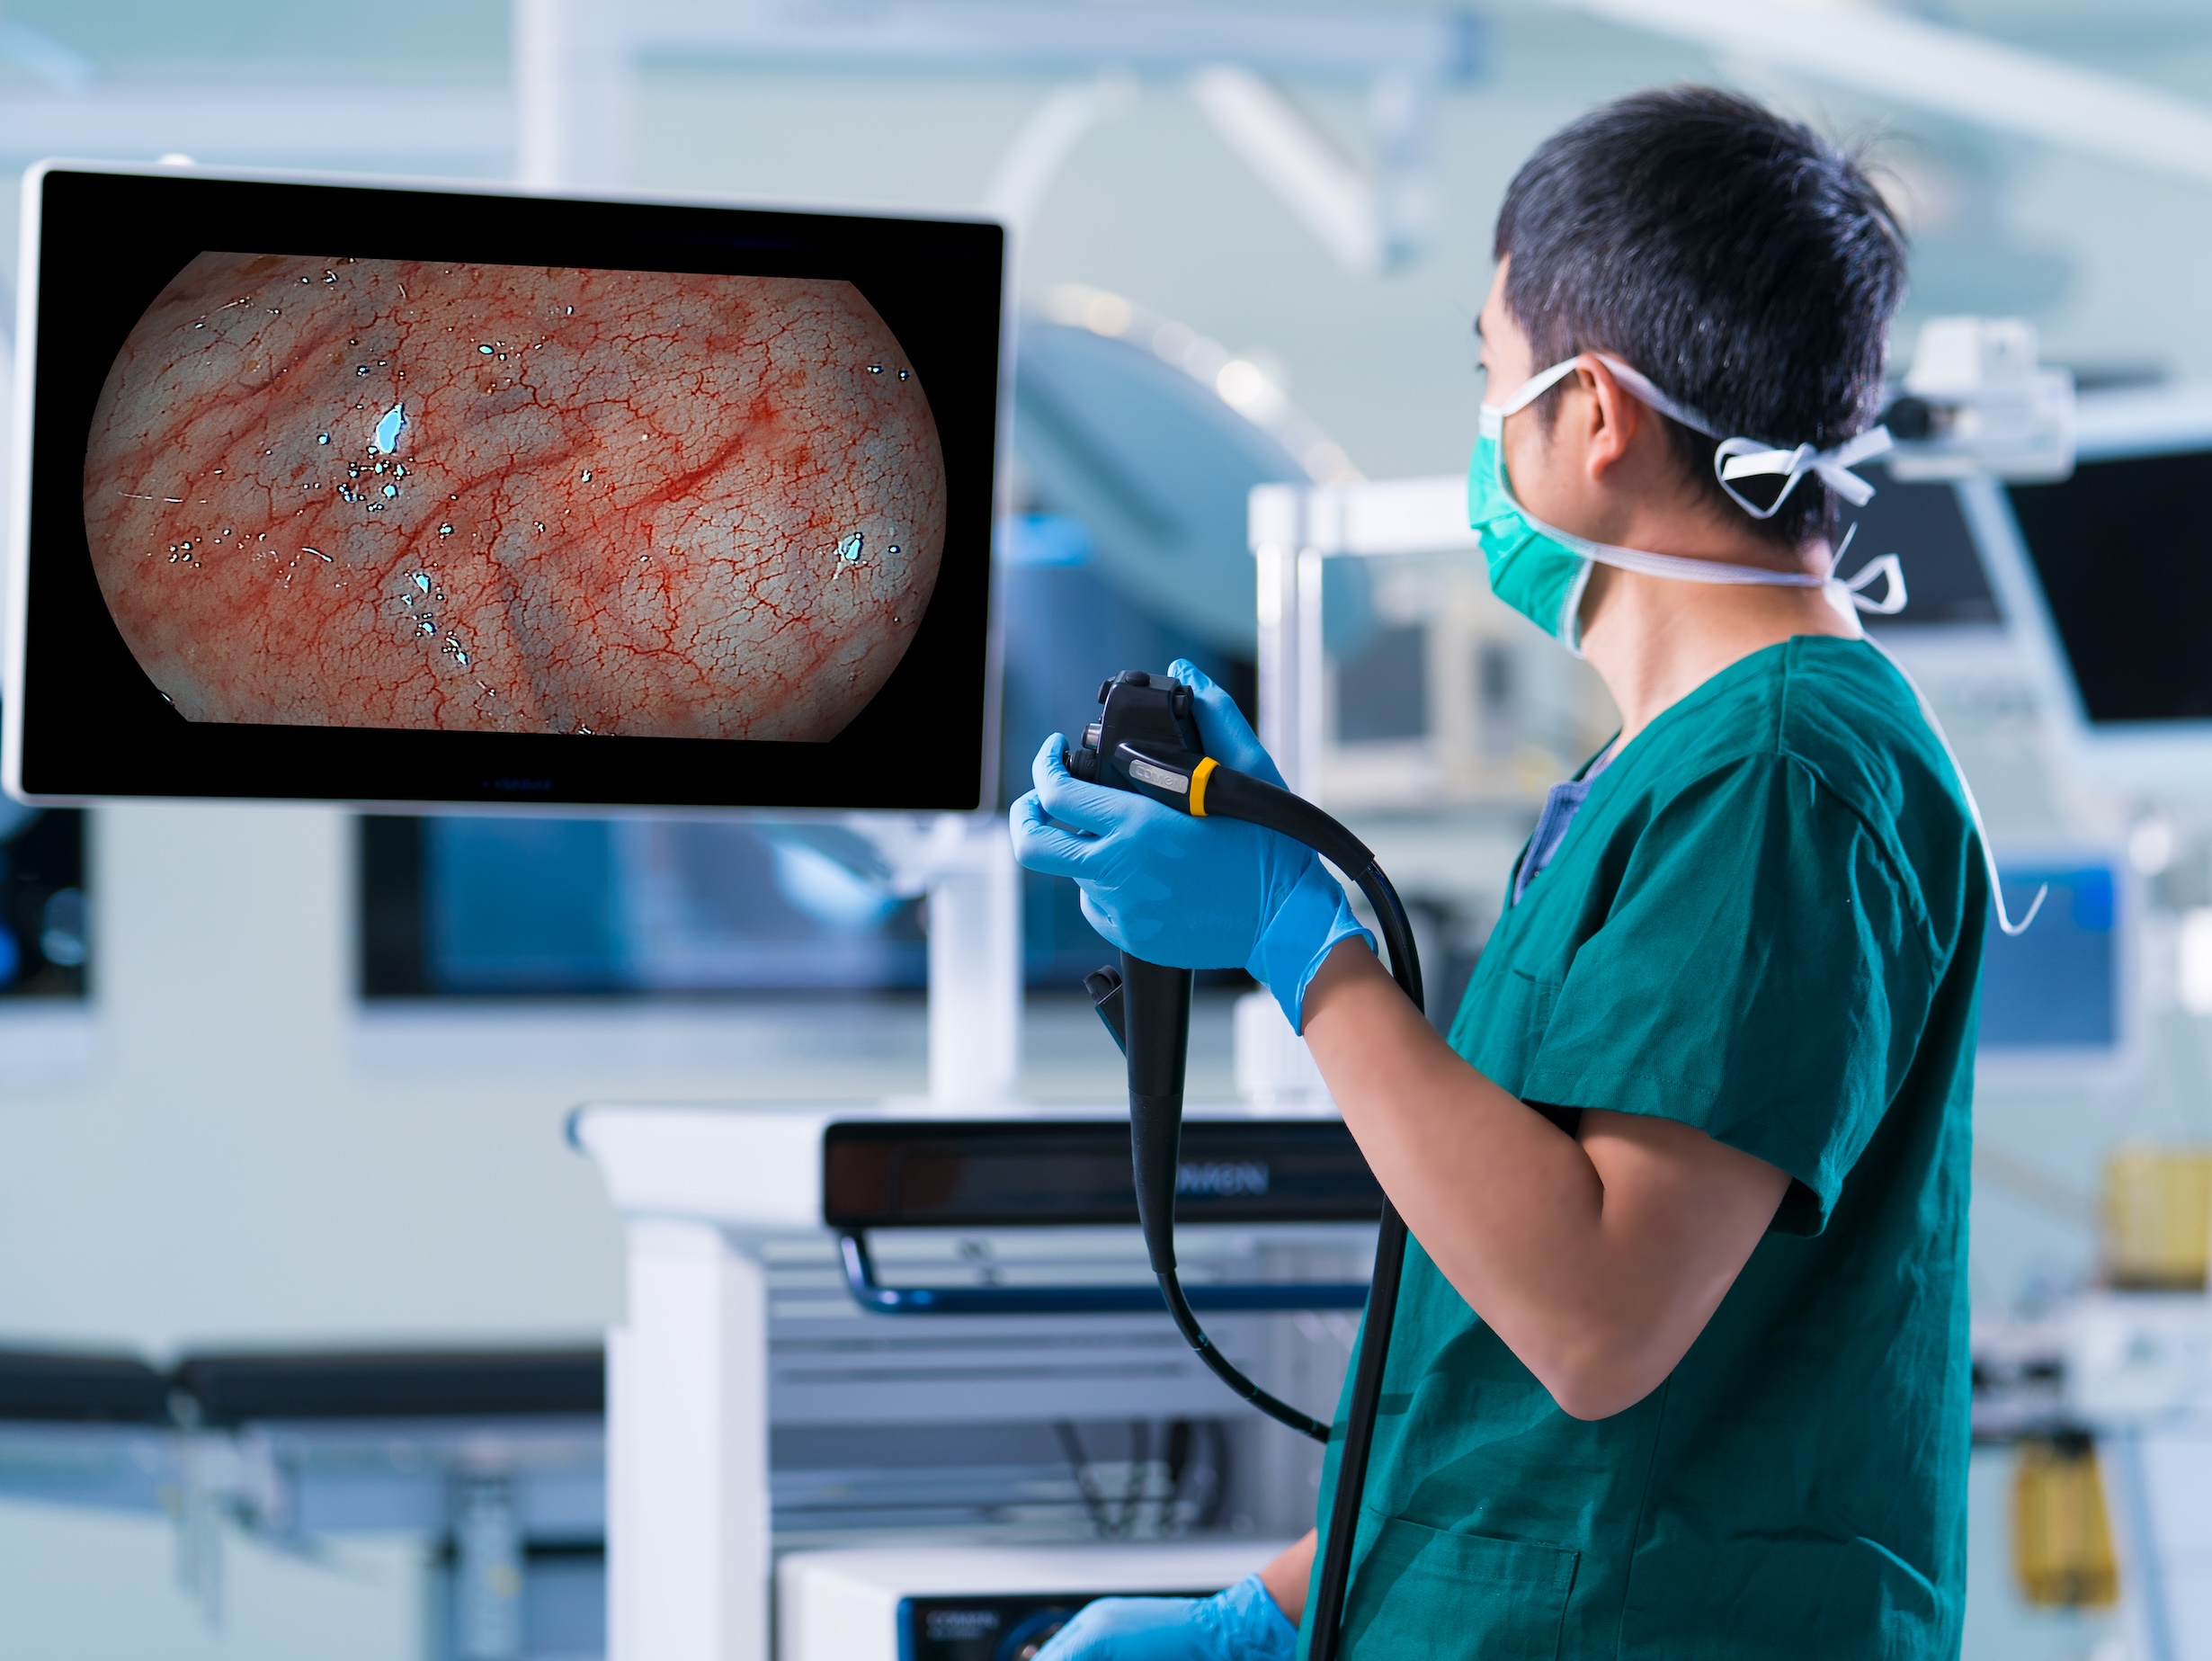
I was on call one March evening in Lisbon when a routine colonoscopy turned into a lesson: dense adhesions, tight angulation, and a scope that just wouldn’t track. During that scenario I noted a measurable delay—procedures ran roughly 30% longer under those conditions; does modern endoscope imaging deserve better? Right there, the role of a video endoscope felt obvious: clearer optics, smoother articulation, less time fumbling—no kidding, that matters to patients and staff alike.
Which workflow steps fail most?
I want to be blunt: many units still treat visualization as an afterthought. From my 15+ years advising hospital endoscopy teams, I’ve seen the same pattern—outdated light sources, poor optical resolution, and cramped biopsy channels (that 2.8mm channel on older flexible models is a choke point). In a 2019 install at a private clinic in Lisbon, swapping a tired flexible video endoscope and a mono-chrome monitor for a modern setup with HD imaging and LED illumination cut average procedure time by 18% on day cases. That specific improvement matters—lower sedation time, faster turnover, fewer cancelled lists. Yet procurement often focuses on sticker price rather than how articulation and imaging interact in real procedures.
Deeper problem: traditional solutions and hidden pains
I’ve watched teams adapt to the same predictable flaws: awkward ergonomics, inconsistent illumination across the field of view, and systems that complicate documentation. Those are not abstract complaints. For example, when an endoscope lacks true wide dynamic range, blood or fluid on the lens reduces contrast and forces repeat suctioning—more pauses, more risk. I once recorded three back-to-back ERCPs where lagging image processing added 45 seconds per cannulation attempt (that adds up). The real pain point is workflow friction: staff shuttling between rooms, manual image capture, and devices that don’t talk to PACS smoothly. We patch these with workarounds—tape, improvised adapters, odd cable runs—but the underlying design hasn’t always prioritized the clinical sequence (and that’s a design choice, not fate).
Forward-looking comparison: technical upgrades that change outcomes
Now, if we look at components critically, improvements become tangible. Better optical resolution plus real-time noise reduction reduces the need for repeat passes. Improved articulation mechanics shorten negotiation through tortuous anatomy. A modern video endoscope with an integrated HD imaging pipeline and streamlined I/O reduces procedural delays at the touchpoints that matter most: insertion, biopsy, and documentation. Technically speaking, upgrading to sensors with higher signal-to-noise ratio and processors with lower latency transforms a sluggish system into one that feels immediate—operators trust it more, and trust reduces defensive, conservative maneuvers that prolong procedures. But—wait—implementation matters: if the monitor calibration is off or the staff aren’t trained on the new articulation thresholds, gains evaporate. I’ve taught teams two-hour practical sessions and seen the difference the next week (real, measurable: faster set-up, fewer camera lens wipes).
What’s Next?
Here’s how I evaluate vendors and systems now, in practical terms: first, test for true optical resolution in clinical lighting (not just lab specs). Second, measure ergonomics—how many clicks to change mode, how the scope sits in hand after an hour. Third, confirm integration: can images and clips move to PACS without manual export? Those are concrete checks I run on site. If you want a checklist: 1) optical resolution under blood-contaminated views; 2) articulation torque and return-to-neutral; 3) end-to-end data flow to hospital records. These three metrics cut through marketing claims and show real performance differences.
I speak from hands-on work: hospital assemblies in Lisbon, an on-call night that taught me patience, and years of procurement conversations where I learned what actually saves time. Choose smartly—measure, test, and demand the right specs. Small investments in imaging and mechanics pay back in nurse hours, patient comfort, and reduced cancellations. (Trust me—I’ve logged the numbers.) Final note: when you shortlist systems, include field tests during peak lists; it’s the only way to see true performance. For practical sourcing and a trusted partner in imaging solutions, see COMEN.